
Table of Contents
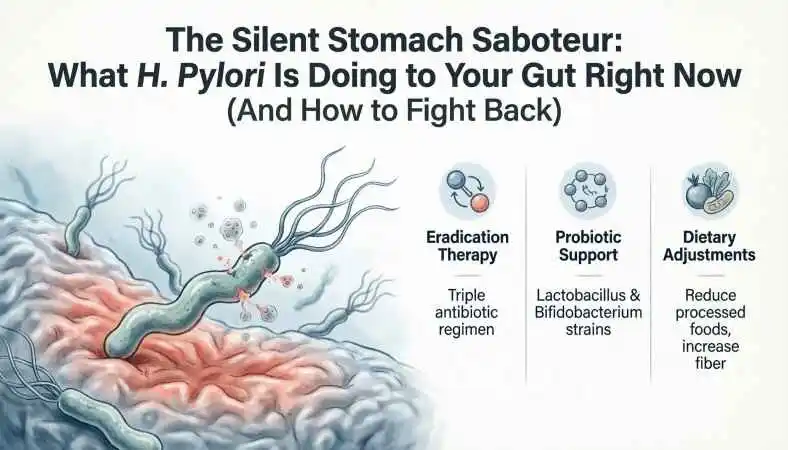
The Silent Stomach Saboteur: What H. Pylori Is Doing to Your Gut Right Now (And How to Fight Back)
Introduction
Imagine a tiny, spiral-shaped bacterium that has silently colonized the stomachs of nearly half the world’s population. It doesn’t announce itself. It doesn’t cause dramatic symptoms at first. It simply burrows into the protective lining of your stomach. It begins a slow, patient process of destruction — one that, left unchecked, can lead to painful ulcers, chronic gastritis, and in some cases, stomach cancer.
Meet Helicobacter pylori — better known as H. pylori — arguably one of the most successful and widespread bacterial infections in human history.
For decades, doctors believed stomach ulcers were caused by stress and spicy food. Then, in 1984, Australian physician Barry Marshall did something extraordinary: he drank a solution teeming with H. pylori bacteria to prove the medical establishment wrong. Within days, he developed gastritis. The discovery earned him and his colleague Robin Warren the Nobel Prize in Physiology or Medicine in 2005, and changed gastroenterology forever.
Yet despite being so common and so consequential, H. pylori remain poorly understood by the general public. Many people carry it for years without knowing. Others suffer from recurring digestive problems without ever connecting them to a bacterial infection. And some, tragically, receive a cancer diagnosis that proper screening could have prevented.

This article is your comprehensive guide to H. pylori — what it is, how it spreads, how to recognize it, and most importantly, how to eliminate it and protect your gut for the long term.
What Is H. Pylori? Understanding the Basics
Helicobacter pylori is a Gram-negative, microaerophilic bacterium — meaning it thrives in environments with low oxygen levels, making the human stomach its perfect habitat. Its helical (spiral) shape allows it to drill through the thick mucus layer that lines the stomach wall, where it then attaches to epithelial cells and evades the body’s immune defenses.
What makes H. pylori particularly cunning is its ability to neutralize gastric acid. It produces an enzyme called urease, which converts urea into ammonia and carbon dioxide. The ammonia raises the pH around the bacteria, creating a mini-alkaline bubble that shields them from the stomach’s acidic environment. This is also the principle behind one of the most accurate diagnostic tests — the urea breath test.
Once established, H. pylori can survive in the stomach for decades. It triggers a chronic inflammatory response, which, over time, damages the stomach lining, disrupts normal acid production, and sets the stage for ulcers and, in a smaller percentage of cases, malignancy.
How Common Is H. Pylori Infection?
The numbers are staggering. According to global epidemiological data, approximately 44% of the world’s population is infected with H. pylori. In developing nations — particularly across parts of Africa, South Asia, and South America — prevalence can exceed 70–80%. In higher-income countries, infection rates tend to be lower, hovering around 30–40%, though disparities exist based on socioeconomic status and living conditions.
In India, studies suggest prevalence rates between 60–80%, making it one of the most affected countries globally. Crowded living conditions, shared water sources, poor sanitation infrastructure, and limited access to clean food preparation contribute significantly to this burden.
The majority of infected individuals — roughly 80% — never develop noticeable symptoms. But that silent carriage is deceptive. Damage accumulates over time, and the risk of serious complications grows with the duration of infection.
How Does H. Pylori Spread?
- pylori transmission is not fully understood, but the primary routes include:
Faecal-oral transmission is the most well-established pathway. The bacteria shed in the faces of infected individuals can contaminate water and food, especially in areas with inadequate sanitation.
Oral-oral transmission is also suspected. H. pylori has been detected in saliva and dental plaque, raising the possibility of spread through kissing, shared utensils, or contaminated food handled by an infected person.
Waterborne transmission is particularly relevant in regions where untreated or inadequately treated water is consumed. Rural communities and areas without clean piped water carry a higher risk.
Intrafamilial spread is well-documented. If one family member is infected, others in the same household are at significantly elevated risk, likely due to shared food, water, and close contact.
Children are especially vulnerable, with most infections acquired before the age of 10 — often without symptoms, setting the stage for a lifetime of silent carriage.
Signs and Symptoms: Recognizing H. Pylori Infection
The challenge with H. pylori is that most infections are asymptomatic. However, when symptoms do occur, they can range from mildly uncomfortable to severely debilitating.
Common symptoms include:
- Burning or gnawing stomach pain — often worse on an empty stomach or at night
- Nausea — persistent, often without vomiting
- Bloating and excessive belching — caused by ammonia gas produced by the bacteria
- Loss of appetite — particularly if associated with ulcers
- Frequent burping — a hallmark symptom often dismissed as minor
- Unintentional weight loss — due to reduced appetite and impaired digestion
- Dark or tarry stools — a warning sign of gastrointestinal bleeding
- Vomiting blood — a medical emergency requiring immediate attention
- Feeling full quickly — even after small meals
Many of these symptoms overlap with other gastrointestinal conditions, including irritable bowel syndrome, acid reflux, and functional dyspepsia. This overlap is one reason H. pylori goes undetected for so long in so many people.
Complications of Untreated H. Pylori Infection
Ignoring or missing an H. pylori infection can have serious, long-term consequences:
Peptic Ulcers
- pylori is responsible for approximately 70–80% of gastric ulcers and up to 90% of duodenal ulcers. The bacteria damage the protective mucus lining, allowing stomach acid to erode the underlying tissue. Ulcers cause significant pain and can lead to life-threatening bleeding or perforation.
Chronic Gastritis
Persistent infection leads to chronic inflammation of the stomach lining (gastritis). Over time, this can evolve into atrophic gastritis — a thinning of the stomach wall — which impairs digestion and nutrient absorption.
Gastric Cancer
- pylori is classified as a Group 1 carcinogen by the World Health Organization (WHO). Long-standing infection is associated with a 2–6 times increased risk of developing stomach (gastric) adenocarcinoma. It is also strongly linked to MALT lymphoma — a rare type of stomach cancer affecting lymphoid tissue.
Iron Deficiency Anemia
Chronic blood loss from ulcers, combined with impaired iron absorption due to reduced stomach acid, can lead to iron deficiency anemia — often presenting as fatigue, pallor, and weakness.
Vitamin B12 Deficiency
Atrophic gastritis caused by H. pylori impairs the production of intrinsic factor, a protein essential for B12 absorption, leading to deficiency with neurological and hematological consequences.
Diagnosis: How Is H. Pylori Detected?
Modern medicine offers several accurate methods to detect H. pylori:
Non-invasive Tests
Urea Breath Test (UBT): The gold standard for non-invasive diagnosis. The patient swallows a urea solution labelled with a carbon isotope. If H. pylori is present, its urease enzyme breaks down the urea, releasing labelled carbon dioxide that is detected in exhaled breath. Accuracy exceeds 95%.
Stool Antigen Test (SAT): Detects H. pylori antigens (proteins) in a stool sample using monoclonal antibodies. Highly accurate and widely used for both diagnosis and confirming eradication after treatment.
Blood Antibody Test: Detects IgG antibodies to H. pylori in the blood. However, antibodies can persist for months after successful eradication, making this test unsuitable for confirming clearance.
Invasive Tests (via Endoscopy)
Rapid Urease Test (RUT): A biopsy sample from the stomach lining is placed in a urea-containing medium. A color change indicates H. pylori presence. Fast and reliable.
Histology: Biopsy samples are examined under a microscope to detect the bacteria and assess the degree of gastric damage.
Culture and Sensitivity: Growing H. pylori from a biopsy sample in a laboratory. The most specific test is uniquely able to determine antibiotic resistance — particularly useful when standard treatment fails.
Treatment: Eradicating H. Pylori
The good news is that H. pylori is treatable. The bad news is that no single antibiotic is effective alone, and resistance is rising globally.
Standard Triple Therapy (7–14 days)
The most widely used first-line regimen consists of:
- A Proton Pump Inhibitor (PPI) (e.g., omeprazole, pantoprazole) — reduces stomach acid to enhance antibiotic efficacy
- Clarithromycin
- Amoxicillin (or metronidazole if penicillin-allergic)
Quadruple Therapy (10–14 days)
Used where clarithromycin resistance is high or when triple therapy has failed:
- PPI
- Bismuth subsalicylate
- Metronidazole
- Tetracycline
Concomitant Therapy
All four antibiotics (PPI + clarithromycin + amoxicillin + metronidazole) given simultaneously — increasingly favored in areas of high resistance.
Bismuth-Based Sequential Therapy
Antibiotics are given in two sequential phases, often with bismuth, shown to achieve higher eradication rates in certain populations.
Confirming Eradication
Treatment completion is not the finish line. A follow-up urea breath test or stool antigen test — performed at least four weeks after completing antibiotics and two weeks after stopping PPIs — is essential to confirm the bacteria have been eliminated.
Eradication rates with modern regimens typically range from 85–95%, though antibiotic resistance (particularly to clarithromycin and metronidazole) is an increasing challenge worldwide.
Diet, Lifestyle, and Natural Approaches
While antibiotics remain the only proven cure, certain dietary choices may reduce H. pylori’s virulence or support gut healing during and after treatment.
Foods with evidence of benefit:
- Broccoli sprouts — rich in sulforaphane, shown to inhibit H. pylori growth in studies
- Green tea — catechins have demonstrated antibacterial effects in laboratory settings
- Manuka honey — contains hydrogen peroxide and methylglyoxal with antimicrobial properties
- Cranberry juice — may inhibit H. pylori adhesion to stomach cells
- Garlic — contains allicin, which has demonstrated anti-H. pylori activity
Foods and habits to avoid during infection:
- Alcohol — irritates the stomach lining
- Spicy, acidic, or fried foods — exacerbate symptoms
- Smoking — significantly impairs healing and increases ulcer risk
- NSAIDs (e.g., ibuprofen, aspirin) — further damage the stomach lining and increase bleeding risk
Probiotics, particularly Lactobacillus strains, have been shown in multiple studies to reduce H. pylori density and mitigate the gastrointestinal side effects of antibiotic therapy. They don’t eliminate the bacteria, but they support treatment tolerability and gut recovery.
Prevention: Protecting Yourself and Your Family
Given its transmission routes, prevention focuses on hygiene and environmental factors:
- Wash hands thoroughly — especially before eating and after using the toilet
- Drink clean, treated water — boil or filter water in areas with questionable supply
- Avoid undercooked or improperly stored food
- Don’t share utensils, cups, or food — particularly important in households with a known infected member
- Maintain dental hygiene — H. pylori has been found in dental plaque
- Treat infected family members — to break the chain of intrafamilial transmission
- Test-and-treat strategies in high-prevalence areas are being explored as public health interventions, particularly in populations at elevated cancer risk
Vaccine development for H. pylori has been an active area of research for decades. While a fully effective vaccine remains elusive, several candidates are in clinical trials, offering hope for future population-level prevention.
- Pylori and Mental Health: The Gut-Brain Connection
Emerging research has begun to explore the relationship between H. pylori and mental health. The gut-brain axis — the bidirectional communication network between the gastrointestinal tract and the central nervous system — means that gut inflammation and dysbiosis can influence mood, cognition, and mental well-being.
Some studies have found associations between H. pylori infection and increased rates of depression and anxiety, though causality remains unclear. What is known is that chronic pain, nutritional deficiencies (particularly B12 and iron), and persistent inflammation — all consequences of H. pylori — can independently contribute to psychological distress.
Treating H. pylori may, in some patients, result in improvements in mood and energy levels, particularly where nutritional deficiencies have been corrected.
When to See a Doctor
Do not wait for symptoms to become severe. Seek medical evaluation if you experience:
- Persistent stomach pain or discomfort lasting more than a few days
- Unexplained weight loss
- Difficulty swallowing
- Persistent nausea or vomiting
- Black or tarry stools
- Blood in vomit
- A family history of stomach cancer or ulcers
- Anemia without clear cause
If you live in a high-prevalence region like India and have never been tested, a conversation with your gastroenterologist about H. pylori screening is worthwhile — especially if you have any digestive concerns.
Conclusion
- pylori is a master of stealth, thriving silently in millions of stomachs across the world. But knowledge is the most powerful weapon against it. Understanding how this bacterium operates, recognizing its symptoms, pursuing timely diagnosis, and completing proven treatment can mean the difference between decades of chronic gut suffering — or worse — and a healthy, functioning digestive system.
The stomach is not just an organ of digestion; it is a gateway to overall health. Protect it. Get tested if you have concerns. And if you’re diagnosed with H. pylori, take heart: this is one of the most treatable chronic bacterial infections known to medicine.
Your gut health is not a background concern — it is central to your energy, immunity, mental clarity, and long-term vitality. Don’t let a silent saboteur rob you of it.
Frequently Asked Questions
- What is H. pylori?
Helicobacter pylori (H. pylori) is a spiral-shaped, Gram-negative bacterium that infects the lining of the stomach and upper small intestine, causing inflammation and, in some cases, ulcers or cancer.
- How common is H. pylori infection?
It affects approximately 44% of the global population — an estimated 3.5 billion people — making it one of the most prevalent chronic bacterial infections in the world.
- How does H. pylori spread?
It spreads primarily through contaminated food, water, and close contact with infected individuals via faecal-oral and oral-oral routes.
- Can H. pylori be transmitted through kissing?
Potentially yes. H. pylori has been found in saliva and dental plaque, suggesting oral-oral transmission is possible, though this route is considered less common than faecal-oral transmission.
- What are the most common symptoms of H. pylori?
Many people have no symptoms. When symptoms occur, they include burning stomach pain, nausea, bloating, belching, and loss of appetite.
- Can H. pylori be present without any symptoms?
Yes. Approximately 80% of infected individuals never develop noticeable symptoms, yet remain at risk for long-term complications.
- How is H. pylori diagnosed?
Diagnosis can be made via urea breath test, stool antigen test, blood antibody test, or endoscopic biopsy with rapid urease test or histology.
- Which diagnostic test is most accurate?
The urea breath test (UBT) and stool antigen test are considered the most accurate non-invasive tests, with sensitivity and specificity above 95%.
- Is H. pylori the cause of all stomach ulcers?
Not all, but most. H. pylori accounts for approximately 70–80% of gastric ulcers and up to 90% of duodenal ulcers. NSAID use is the other major cause.
- Can H. pylori cause stomach cancer?
Yes. H. pylori is a WHO-classified Group 1 carcinogen linked to gastric adenocarcinoma and MALT lymphoma. It increases stomach cancer risk by 2–6 times.
- Is H. pylori curable?
Yes. With appropriate antibiotic therapy (usually triple or quadruple regimens) combined with a proton pump inhibitor, eradication rates of 85–95% are achievable.
- What antibiotics are used to treat H. pylori?
Commonly used antibiotics include clarithromycin, amoxicillin, metronidazole, and tetracycline, typically combined with a proton pump inhibitor.
- How long does H. pylori treatment take?
Standard treatment courses range from 7 to 14 days, depending on the regimen chosen and local antibiotic resistance patterns.
- What happens if H. pylori is not treated?
An untreated infection can lead to chronic gastritis, peptic ulcers, gastrointestinal bleeding, and in some cases, stomach cancer.
- Can H. pylori come back after treatment?
Reinfection is possible, particularly in high-prevalence environments. Recurrence rates are low in developed countries (1–2% per year) but higher in developing regions.
- How do I confirm H. pylori has been eradicated?
A urea breath test or stool antigen test should be performed at least four weeks after completing antibiotics and two weeks after stopping PPIs to confirm eradication.
- Can children get H. pylori?
Yes. Most infections are acquired in childhood, often before the age of 10. Children in low-income households or crowded living conditions are at the highest risk.
- Does H. pylori affect nutritional status?
Yes. It can cause iron deficiency anemia by causing blood loss and impairing iron absorption, and vitamin B12 deficiency through atrophic gastritis affecting intrinsic factor production.
- What foods should I avoid with H. pylori?
Avoid alcohol, spicy and acidic foods, fried foods, processed meats, and carbonated drinks as they can worsen symptoms and delay healing.
- Are there natural remedies for H. pylori?
Broccoli sprouts (sulforaphane), manuka honey, garlic, green tea, and cranberry juice show some evidence of anti-H. pylori activity, but they do not replace antibiotic therapy.
- Can probiotics help with H. pylori?
Probiotics, particularly Lactobacillus strains, may reduce H. pylori density and ease antibiotic-related side effects. They are a helpful adjunct but not a standalone treatment.
- Why is antibiotic resistance a concern with H. pylori?
Clarithromycin and metronidazole resistance is increasing globally, reducing the effectiveness of standard triple therapy. Resistance patterns vary by region, influencing treatment choices.
- Is H. pylori testing recommended for everyone?
Not universally. Testing is recommended for people with peptic ulcer disease, unexplained dyspepsia, a family history of gastric cancer, or in certain high-risk populations.
- Can H. pylori affect mental health?
Emerging evidence suggests associations between H. pylori and depression or anxiety, possibly mediated through the gut-brain axis, chronic inflammation, and nutritional deficiencies.
- Does H. pylori infection increase risk for other cancers?
- pylori is primarily associated with gastric cancer and MALT lymphoma. Evidence for other cancer associations (e.g., colorectal or pancreatic) exists but is less conclusive.
- Is there a vaccine for H. pylori?
Not yet available commercially. Several vaccine candidates are in clinical development, with some showing promising results in trials, but no approved vaccine currently exists.
- Can H. pylori cause bad breath?
Yes. The ammonia produced by H. pylori’s urease activity can contribute to halitosis (bad breath), which may improve significantly after successful eradication.
- Should I test my family members if I am diagnosed with H. pylori?
Yes, particularly if close family members have symptoms. Testing and treating infected family members help break the chain of intrafamilial transmission and prevent reinfection.
- Is H. pylori more common in any particular group?
Prevalence is higher in older adults, people from low-income backgrounds, residents of developing countries, those with crowded living conditions, and individuals with poor access to clean water and sanitation.
- Can I live a normal life with H. pylori?
Most infected people never know they have it and live normally. However, untreated infection carries real risks over time. Diagnosis and treatment can prevent serious complications and significantly improve quality of life.
⚕️Medical Disclaimer:
The information provided on this website is for general educational and informational purposes only and is not intended as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.
